

StrongMinds

StrongMinds
Treating depression at scale in sub-Saharan Africa, with free group therapy delivered by trained members of the community.

Click any figure to learn how we worked it out
Cost-effectiveness
The cost-effectiveness of StrongMinds is $25 per WELLBYOne WELLBY is equivalent to a 1-point increase on a 0-10 wellbeing scale for one year. Read more. This means that for every $1,000 donated, the organisation creates 40 WELLBYs.
Put another way, every $32 donated prevents the equivalent of a year of depression avertedDepression is associated with about 1.3 points less life satisfaction, so averting a year of it is worth about 1.3 WELLBYs. Read more (a YODA) for someone.
We calculate the cost-effectiveness by pairing the estimated effect for each charity with the estimated cost to deliver the intervention.
Impact
We estimate StrongMinds has an overall effect of 1.80 WELLBYs on the individual recipient and their household. Because improving one person’s mental health can benefit those close to them, the household effect includes an estimated 16% spilloverThe effects on other individuals, such as those in the household, who did not receive the intervention but may nonetheless benefit. Read more to household members, over time.
How we arrived at it
To estimate the impact of StrongMinds, we combined general evidence of the impact of psychotherapy on subjective wellbeing in low- and middle-income countries with evidence directly evaluating the impact of StrongMinds’ programme: 1 RCT related to StrongMindsThis is the Baird et al. (2024) RCT. We discuss its limited relevance in the FAQs. and StrongMinds’ monitoring and evaluation pre-post data.
For the general evidence we first conducted a systematic reviewA search designed to capture every relevant study on a topic, following inclusion criteria set in advance. Read more to gather general evidence on the impact of psychotherapyWe defined psychotherapy as an intervention with a structured, face-to-face talk format, grounded in an accepted and plausible psychological theory, and delivered by someone with some level of training. on subjective wellbeing in low- and middle-income countries. After excluding outliers and ‘high risk of bias’ studies, we collected 84 RCTs with a sample of 25,363 unique participants.
We then estimated the effects in each source using a meta-analysisA statistical method for combining the results of many studies, weighting each by its precision. Read moreFor each psychotherapy intervention, we extract every follow-up over time for every outcome measure that fits our inclusion criteria. This means that there is dependency (i.e., non-independence) between the effect sizes within an intervention between outcomes collected for a certain timepoint, and between timepoints for a given intervention. We select a 3-level (random effects) model to account for this dependency.. We measured the effect from each study using Hedges’ g standardised mean differencesThe SMD is the difference between the group averages in terms of SD units. Read moreOur preferred measures of wellbeing are self-reported life satisfaction or happiness, but many of the studies we found used measures of affective mental health (MHa; i.e., depression, general anxiety, or general distress). Standard deviations of MHa were converted to standard deviations of wellbeing using a 1:1 conversion. See our cost-effectiveness methodology and Dupret et al. (2024) for more detail.. Effects in standard deviations are turned into WELLBYs by multiplying by the typical spread of a 0-10 wellbeing scale, about 2 points. For the pre-post data we use a pseudo-synthetic controlA stand-in comparison group built from other evidence, used where monitoring data has no control group. Read more method to deal with the lack of control group.
Some studies measured the impact of psychotherapy at different time points. We used this information to estimate the total effect of psychotherapy over time using a meta-regression modelMeta-regressions are like regressions, except the data points (i.e., dependent variables) are effect sizes weighted according to their precision and the explanatory variables are study characteristics. Meta-regressions allow us to explore why effects might differ between studies; in this case, we examine how effects differ depending on the length of time to the follow-up. that assumes the benefits decline at a constant rate over time.
After estimating the total recipient effect over time, we adjust our estimates for internal validity (publication biasA systematic error that occurs when the outcome of a study influences whether or not it is published. Read more, range restriction, response bias, and a replication adjustment for StrongMinds’ own monitoring data, which is not causal) and for external validity (dosage and other characteristics of the charity).
Then, because improving one person’s mental health can benefit others who are close to that person, we also estimated the spillover effects on household members (i.e., operationalised as a 16% spillover ratio). Thus, the overall household effect includes the estimated impact on recipients and household members over time.
We then calculate a final effect estimate for each charity by combining the three estimates from different evidence sources, using informed subjective weights (i.e., we combine weights based on statistical uncertainty using a Bayesian method with subjective adjustments for harder-to-quantify characteristics).
Cost
Based on StrongMinds’ expenditures in 2023, we estimate that it costs $44.56* to provide a course of group therapy to one person, which creates 1.80 WELLBYs.
*StrongMinds’ cost per person is now much lower, below $20. We have yet to incorporate this in our analysis, so the figure above is conservative.
Funding need
$4.0M is how much StrongMinds could absorb right now without it changing their cost-effectiveness. Every dollar of that gap buys roughly the same wellbeing as the last one did.
StrongMinds runs its own fundraising targets, which are larger. The figure here is a different quantity: not what they are trying to raise, but how much more they could take on today at the cost-effectiveness we have estimated.
Quality of evidence: Low to Moderate
Quality of evidence is about the world: how much the studies that exist can tell us about StrongMinds’ programme.
Our quality of evidence assessment is stringent. We assess quality of evidence according to an adapted version of the ‘GRADE’ criteria, a widely used and rigorous tool for assessing evidence quality across healthcare and research fields. As a result, we expect very few interventions that we evaluate for wellbeing in LMICs (which tend to be less well-studied) will score more than ‘moderate’ on the quality of their evidence. Considering most decisions about charities are made with little-to-no evidence, this is a substantial improvement.
- General meta-analysis of psychotherapy: moderate. 84 RCTs with low (43%) or some (57%) risk of biasThe chance that a study’s design or conduct has distorted its result, rated with the Cochrane tool. Read more (high risk of bias studies were removed). Some inconsistency in effects, limited relevance, and some publication biasA systematic error that occurs when the outcome of a study influences whether or not it is published. Read more (which we adjust for).
- SM RCT (Baird et al.): low. 1 RCT with some risk of bias. Issues with relevance (see outstanding uncertainty). Moderate imprecision. Major inconsistency (because we cannot verify with one study). No concern about publication bias.
- SM M&E: very low. Very relevant, but synthetic control provides limited information. Potential for substantial risks of bias.
Depth of our analysis: In-depth
Depth of analysis is about our work: how much of the evidence we reviewed and how complete the analysis is.
We believe we have reviewed most or all of the relevant available evidence on the topic, and we have completed nearly all (e.g., 95%+) of the analyses we think are useful.
StrongMinds is one of two organisations we conducted the deepest research on. How we rate evidence and depth.
How uncertain are we?
A deep analysis is not one with low uncertainty.
To quantify the statistical uncertainty in our results, we simulated StrongMinds’ cost-effectiveness thousands of times by varying key parametersThese include: the initial effect and the annual decay rate (which allows for variation in the duration of effects), the household spillover, as well as the household size. to see how the results might differ across a range of reasonable inputs (e.g., Monte CarloRunning thousands of simulations with different possible values for the inputs, to estimate the uncertainty of the outcome. Read more simulations). This is illustrated below.
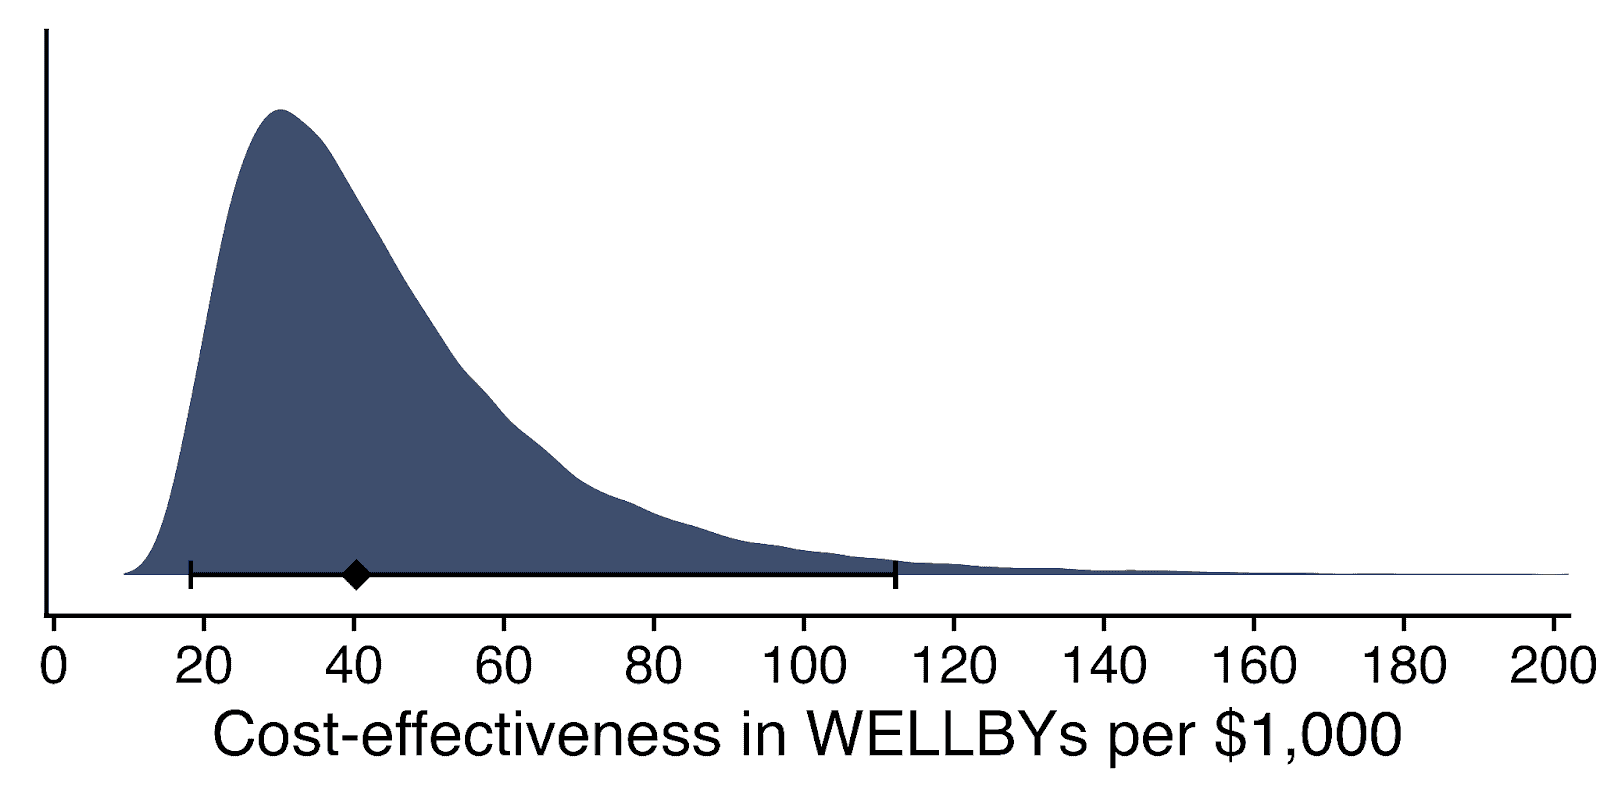
Density plot of the quantified uncertainty around StrongMinds’ cost-effectiveness. Note. The diamond represents the central estimate of cost-effectiveness. The shaded area is a probability density distribution and the whiskers represent the 95% confidence interval.
Why we recommend StrongMinds
StrongMinds is one of the most cost-effective and well-evidenced life-improving charities we have evaluated in depth so far, and we are confident about our analysis. Future research could update our evaluation, but we think it is a particularly good fit for donors who value improving lives.
What StrongMinds does
StrongMinds brings free group therapy to people with depression in Africa who would otherwise get none: six weekly sessions of group interpersonal therapy, run by trained members of the community, mostly through government and NGO partners in Uganda and Zambia. They treated 426,642 people in 2024. Read our interview with StrongMinds.

Our research about StrongMinds
- 2021Why mental health, and which programmes We identified that mental health was a key global priority in our Mental health cause area report, then evaluated psychotherapy interventions in the Psychotherapy cost-effectiveness analysis, and identified StrongMinds as a promising charity in the Mental health programme evaluation.
- 2021–22Our first StrongMinds analysis, and the comparison with cash We assessed the cost-effectiveness of StrongMinds in the StrongMinds cost-effectiveness analysis, compared it to cash transfers in our Psychotherapy vs cash transfer comparison, and added household spillovers in our household spillover effects report.
- November 2023A full re-analysis of psychotherapy A substantial update to our psychotherapy analysis and StrongMinds evaluation: systematically reviewing the literature, updating the evidence for the individual and household effects, correcting for publication bias, and combining the general and charity-specific evidence using Bayesian methods. Note that this is a working paper and will be updated over time.
- April 2024Seeing the groups in Kampala Our director, Michael Plant, undertook a day-long site visit to StrongMinds in Uganda.
- August 2024An interim update We published an interim update.
- November 2024Our deepest analysis yet More importantly, another substantial update. We extracted additional studies, double-checked our extraction, conducted double risk of bias analysis, added monitoring and evaluation pre-post data as a source of evidence, updated how we weight the different sources of evidence, expanded our adjustments, expanded the factors that influence our confidence, and used the latest information from StrongMinds.



Frequently Asked Questions
Does psychotherapy actually work?
Psychotherapy has been shown to be an effective treatment against depression: as good as or better than the alternative of drug treatment in many meta-analyses (Cuijpers et al., 2019). Cuijpers et al. (2016) found that interpersonal therapy does not differ in efficacy from other therapy forms, and Cuijpers et al. (2018) supports the idea that psychotherapy is at least as effective in non-Western countries as Western countries. Singla et al. (2017) also found psychological treatments deployed in LMICs to be an effective way to treat depression.
How does psychotherapy work?
Psychotherapy works by providing people with a safe space to process their thoughts and feelings, and learn adaptive skills to correct their maladaptive thoughts, emotional processing, behaviours, and social interactions. IPT is a time-limited intervention that focuses on addressing stressful life events and interpersonal challenges, while also helping patients connect with new social supports and improve existing relationships (Weissman et al., 2007; Ravitz & Watson, 2014).
Is poor mental health only a problem for high-income countries?
No, the idea of the ‘happy poor’ is not accurate: there are about as many people suffering from mental health problems in LMICs as in HICs (Our World in Data, 2022). Furthermore, treatment for mental health is especially underfunded in LMICs, and even when it is funded, it can vary considerably in qualityFor example, it’s still relatively common for people with severe mental illnesses in LMICs to be restrained in solitary confinement and given no other treatment. (Walker et al., 2021).
What’s the relationship between mental health and poverty?
Poverty and mental health have a complex bidirectional relationship, where each can worsen the other (Ridley et al., 2020). However, one can be poor without being depressed, and vice versa. Notably, if mental health problems occur because of maladaptive thoughts, behaviours, and social interactions, then these are causes that can be independent from poverty.
Does psychotherapy just make people accept poverty?
No, psychotherapy helps people change maladaptive thoughts, behaviours, and relationships. These can worsen poverty and may not be addressed by alleviating financial burdens – instead, many of these symptoms need specific interventions targeting them, such as psychotherapy. Additionally, mental health interventions – and presumably psychotherapy as well – can improve economic outcomes (Lund et al., 2022)In fact, the authors find in a quick calculation that mental health interventions are more cost-effective than cash transfers at improving economic outcomes (p. 32)..
Shouldn’t we just give people cash, so they can decide whether to buy therapy, or something else, for themselves?
One perspective that’s common among economists is that people are the best judges of what’s good for them. While this may be true in theory, in the real world, people have imperfect information and inadequate options, and other barriers (such as stigma around seeking mental health treatment) may get in the way. The advantage of the WELLBY approach is that, through people’s self-reports, we get evidence on what actually makes a difference to their lives as they live them – not just what they expect would matter. Using these self-reports, our analyses indicate that providing a depressed person with therapy improves happiness more than giving them, or another non-depressed person, the cash equivalent to the cost of that programme.
What if people are just saying they feel better because they think it’ll benefit them, or someone else, materially?
This is a concern about a type of response bias called ‘experimenter-demand effects’, where respondents shift their behaviour in response to their guess of what the study is about. The available evidence we’ve found suggests this is not a major concern, and it likely applies to all research with self-reported outcomes (i.e., it is not specific to psychotherapy). However, the research on the question has been sparse and may not address all concerns, so we’d be interested in seeing more research on this topic.
Isn’t Baird et al. (2024) just the most relevant study to use?
The Baird et al. trial found a small effect. However, despite the trial taking place in Uganda (where StrongMinds operates) and using a version of StrongMinds’ model, there are several ways in which the Baird et al. study is different from StrongMinds’ actual programme in the field today, which means we cannot generalise from it as much as one might expect. This was the first time StrongMinds had attempted to implement its programme conducted via a new partner. The study involved adolescents receiving therapy from other young people (StrongMinds primarily does therapy for adults led by adults). The facilitators were inexperienced and given insufficient supervision. Attendance was low, with 44% of participants failing to attend any sessions. Furthermore, the long-term data collection overlapped with COVID. These issues are noted by Baird et al. (2024) and/or StrongMinds themselves (StrongMinds, 2024). We give an appreciable, but limited, weight to this source of evidence: 20% of the total, with the remaining 80% coming from the meta-analysis and the monitoring and evaluation data because we think these other sources of evidence are informative as well.
What’s the relationship between HLI and StrongMinds?
HLI and StrongMinds are completely independent organisations. We are not paid by StrongMinds, and would never accept money to recommend any organisation.
Is your question missing from this list? Contact us at hello@happierlivesinstitute.org.
Support the important work StrongMinds does
A donation here buys a course of group therapy for someone living with depression, and a year of life they would otherwise have spent unwell.